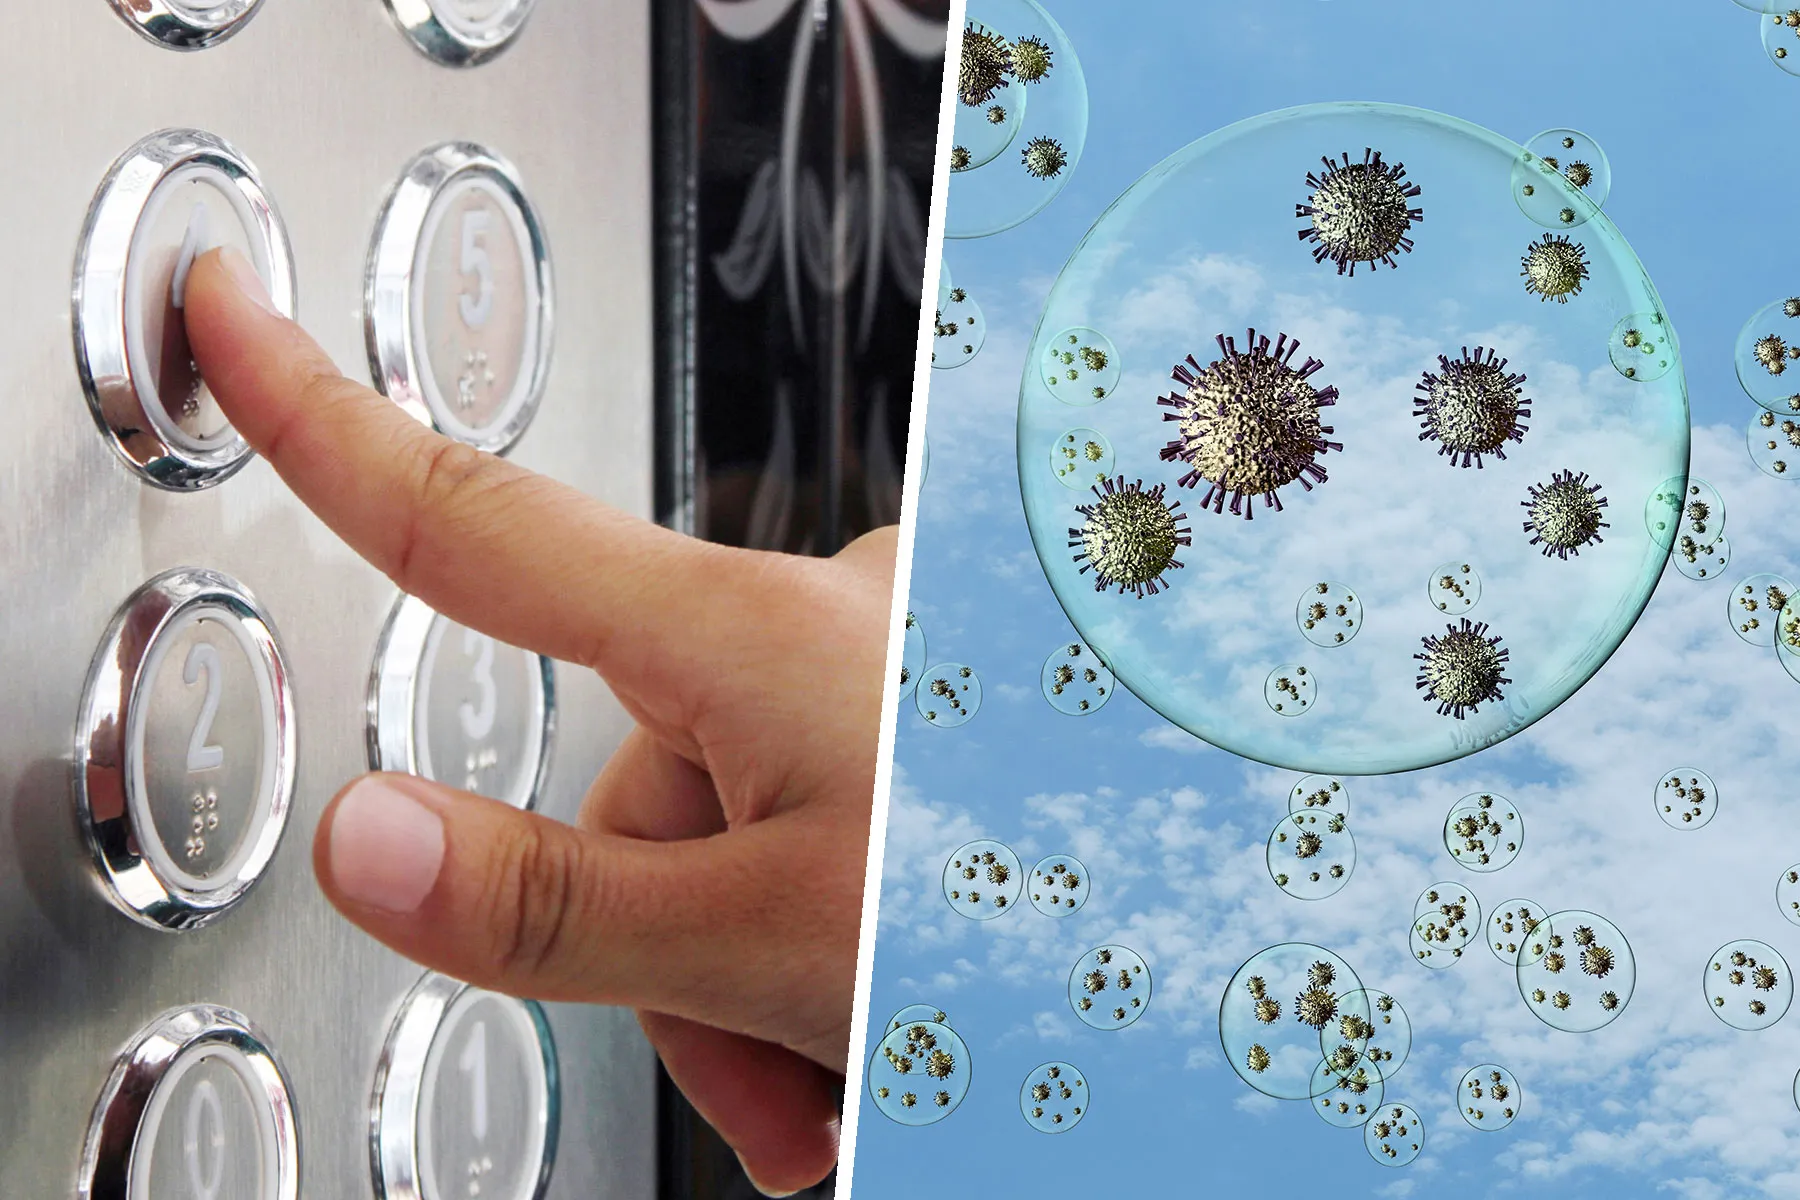
Germs are tiny, but their travel plans can be surprisingly elaborate. Some move through a handshake, a kiss, an open cut, or a shared towel. Others hitch a ride on particles released when people breathe, talk, cough, sing, or sneeze. A few are annoyingly versatile and use more than one route, like microscopic commuters refusing to commit to a single train line.
Understanding direct contact vs. airborne illness is more than a vocabulary exercise. The route of transmission determines which prevention steps matter most. Handwashing and avoiding shared personal items can be powerful against contact spread, while cleaner indoor air, well-fitting masks, distance, and vaccination may be more important when infectious particles can be inhaled.
This guide explains the difference between contact transmission and airborne transmission, where respiratory droplets fit, which illnesses commonly use each route, and how to choose practical precautions without turning your home into a low-budget laboratory.
What Is the Main Difference?
Direct contact transmission occurs when a pathogen passes through physical contact between an infected source and another person. The transfer may involve skin, mucous membranes, wounds, blood, saliva, sexual fluids, or other infectious material. A related category, indirect contact transmission, occurs when germs move through a contaminated object or surface, often called a fomite.
Airborne transmission occurs when infectious particles are released into the air, remain suspended for some period, and are inhaled by another person. These particles can build up indoors, especially in crowded or poorly ventilated spaces. Exposure does not always require touching the sick personor even being beside that person at the exact moment particles are released.
| Feature | Direct Contact Illness | Airborne Illness |
|---|---|---|
| Main pathway | Physical transfer from a person, body fluid, lesion, or infected tissue | Inhalation of infectious particles suspended in air |
| Typical risk factor | Close physical contact, caregiving, sex, shared personal items, or broken skin | Shared indoor air, crowding, prolonged exposure, or weak ventilation |
| Helpful controls | Hand hygiene, wound covering, cleaning, gloves when appropriate, and not sharing personal items | Ventilation, filtration, isolation, well-fitting masks or respirators, and vaccination when available |
| Classic examples | Ringworm and some staph or MRSA infections | Measles, pulmonary tuberculosis, and chickenpox |
Definitions and healthcare transmission categories were synthesized from CDC and OSHA guidance.
How Direct Contact Illness Spreads
Direct contact sounds simple: one person touches another, and a pathogen crosses the biological border. In reality, the details depend on the organism, the part of the body involved, the condition of the skin, and whether enough infectious material reaches a suitable entry point.
Skin-to-Skin Contact
Fungal infections such as ringworm can spread when infected skin touches another person’s skin. Certain bacterial infections, including some caused by Staphylococcus aureus or MRSA, may also spread through contact with infected skin, wounds, or contaminated drainage.
Athletes, wrestlers, caregivers, and household members may face increased exposure because close physical contact is frequent and minor cuts are common. Warm, humid environments can also encourage fungal growth, which helps explain why locker rooms occasionally seem to operate as all-inclusive resorts for ringworm.
Contact With Body Fluids
Some pathogens spread when blood, saliva, semen, vaginal fluids, vomit, feces, or other infectious fluids reach broken skin or mucous membranes. The exact risk varies dramatically by disease and the type of exposure.
Ebola, for example, is associated primarily with direct contact with infected blood or body fluids rather than ordinary airborne spread. Sexually transmitted infections may pass through intimate skin or mucosal contact, sometimes even when no obvious sore is visible.
Indirect Contact Through Contaminated Objects
A germ picked up from a doorknob, towel, razor, toy, phone, piece of sports equipment, or medical device is using indirect contact transmission. The contaminated object is commonly called a fomite.
People often group direct and indirect routes together as “contact spread” because the preventive logic overlaps: clean hands, properly handled equipment, covered wounds, and fewer shared personal items.
Not every contaminated surface causes an infection. The organism must survive long enough, transfer in sufficient quantity, and reach an entry point such as the eyes, nose, mouth, genitals, or damaged skin. A surface can also test positive for genetic material without necessarily containing enough viable pathogen to make someone sick. In other words, a suspicious doorknob is not automatically a supervillain.
Contact-spread examples and distinctions are supported by Cleveland Clinic, Johns Hopkins Medicine, CDC, and NIH resources.
How Airborne Illness Spreads
People release respiratory particles whenever they breathe and speak, not only when they produce an award-winning sneeze. Coughing, shouting, singing, exercising, and heavy breathing may increase the number of particles released.
Larger particles may settle relatively quickly or land on nearby eyes, noses, and mouths. Smaller aerosols can remain suspended, move with air currents, and be inhaled into the respiratory tract.
Airborne risk generally rises when several conditions line up:
- An infectious person is releasing a pathogen.
- The pathogen remains viable in respiratory particles.
- The setting is enclosed or poorly ventilated.
- People are close together or exposure is prolonged.
- A susceptible person inhales a sufficient infectious dose.
Outdoor transmission is usually less efficient because moving air dilutes infectious particles. However, close-range exposure can still occur outdoors, particularly during prolonged face-to-face conversation or crowded events.
Classic Airborne Diseases
Measles is one of the clearest examples of an airborne infection. Its virus can remain infectious in the air of an enclosed space after an infected person has left.
Pulmonary tuberculosis spreads when people inhale airborne particles containing Mycobacterium tuberculosis. Risk is especially associated with repeated or prolonged exposure in enclosed spaces.
Chickenpox can spread through airborne respiratory particles and through direct contact with fluid from chickenpox blisters. This is a useful reminder that pathogens do not always respect the tidy categories people create for them.
Respiratory Viruses May Use Multiple Routes
COVID-19, influenza, respiratory syncytial virus, and common-cold viruses do not always fit neatly into a single transmission box. Depending on the virus and circumstances, spread may involve inhaled aerosols, short-range respiratory particles deposited on mucous membranes, direct contact with respiratory secretions, or contaminated hands and surfaces.
One route may be more important than the others without being the only possible route. That is why arguing that an infection is “airborne or droplet” can be less useful than asking which measures reduce exposure in the actual setting.
In a crowded room with closed windows, air-focused precautions deserve attention. While caring for a child with a runny nose who has converted every toy into a glossy biological sample, hand hygiene and targeted cleaning matter too.
Airborne behavior, classic examples, and mixed respiratory-virus routes are supported by CDC, NIH, EPA, Mayo Clinic, and Johns Hopkins Medicine.
Where Do Respiratory Droplets Fit?
Traditional infection-control language separates droplet transmission from airborne transmission. Droplet precautions focus on respiratory particles that tend to cause infection at close range, particularly when they land on the eyes, nose, or mouth. Airborne precautions focus on particles capable of remaining suspended and being inhaled over time.
Modern aerosol science shows that exhaled particles exist on a continuum rather than in two perfectly behaved sizes. Their movement depends on particle diameter, humidity, airflow, temperature, ventilation, filtration, and how forcefully they were released.
A respiratory particle does not stop at an invisible six-foot border and consult a rulebook. Distance can reduce exposure, but distance alone is not a force field.
When an infection spreads through respiratory particles, a combination of shorter exposure, fewer occupants, cleaner air, filtration, source control, and appropriate masking is generally stronger than relying on one spacing rule.
Droplet and airborne precaution concepts are supported by CDC isolation guidance, OSHA workplace guidance, and NIH aerosol reviews.
Direct Contact vs. Airborne Illness: Key Risk Factors
Factors That Increase Contact-Transmission Risk
- Frequent skin-to-skin contact
- Open cuts, abrasions, rashes, or surgical wounds
- Contact with infected blood, drainage, or body fluids
- Shared towels, razors, cosmetics, clothing, bedding, or sports equipment
- Inadequate hand hygiene
- Poor cleaning of shared medical or personal equipment
- Caregiving activities involving diapers, wounds, or bodily secretions
Factors That Increase Airborne-Transmission Risk
- Crowded indoor spaces
- Poor ventilation or limited outdoor-air exchange
- Long exposure periods
- Loud talking, singing, shouting, or heavy breathing
- Close proximity to an infectious person
- Airflow that moves contaminated air toward other occupants
- Lack of appropriate respiratory protection in high-risk settings
Personal susceptibility also matters. Age, vaccination status, immune function, chronic medical conditions, and the dose of pathogen received can influence whether exposure leads to infection or severe illness.
Why the Transmission Route Changes Prevention
For Contact Transmission: Break the Touch Chain
- Wash hands with soap and water after caregiving, bathroom use, wound care, diaper changes, coughing, or handling contaminated laundry.
- Use hand sanitizer containing at least 60% alcohol when soap and water are unavailable.
- Cover draining wounds with clean, dry bandages.
- Do not share towels, razors, cosmetics, bedding, sports gear, or clothing when a contagious skin infection is suspected.
- Clean frequently touched objects and follow the disinfectant manufacturer’s instructions.
- Use gloves for anticipated contact with blood, body fluids, wounds, or contaminated materials.
- Clean your hands after removing gloves because gloves are not magical germ force fields.
For Airborne Transmission: Improve the Air
- Increase outdoor-air ventilation when weather, safety, and building conditions permit.
- Use properly maintained HVAC filtration or appropriately sized portable air cleaners.
- Avoid crowded, poorly ventilated indoor spaces when respiratory illnesses are spreading widely.
- Wear a well-fitting mask or respirator when risk is elevated or when caring for someone with a respiratory infection.
- Reduce the amount of time spent in enclosed spaces with a sick person.
- Stay away from others while acutely ill and follow current public-health guidance.
- Keep recommended vaccinations up to date.
The strongest prevention plan is usually layered. Cleaner air cannot sanitize a contaminated bandage, and heroic handwashing cannot remove infectious particles already accumulating in a poorly ventilated room. Match the tool to the routeand use multiple tools when the route is mixed or uncertain.
Prevention recommendations were synthesized from CDC handwashing and masking guidance, EPA ventilation guidance, OSHA, and ASHRAE.
Direct Contact vs. Airborne Illness in Everyday Settings
At Home
When a household member has a contagious skin infection, prioritize wound coverage, separate towels, careful laundry handling, treatment adherence, and hand hygiene. Frequently handled personal items may also need cleaning.
When someone has a respiratory illness, add airflow-focused precautions. Open windows when practical, run exhaust fans, use suitable filtration, reduce close face-to-face time, and consider masks around relatives who have an increased risk of severe disease.
At School or Day Care
Children combine close contact, shared supplies, enthusiastic coughing, and a mysterious resistance to keeping fingers out of noses. Schools therefore need both contact-focused and air-focused measures.
Useful strategies include accessible handwashing, respiratory etiquette, routine cleaning, adequate ventilation, appropriate vaccination, and policies that allow sick students and staff members to remain home.
At Work
During an office respiratory outbreak, polishing every desk while ignoring a packed conference room can create a sparkling but incomplete defense.
Employers should consider ventilation, filtration, room occupancy, remote participation, sick-leave practices, and masks during periods of increased respiratory transmission. Healthcare, laboratory, emergency-response, and other high-risk workplaces may require formal exposure-control and respiratory-protection programs.
At the Gym
Shared mats, benches, towels, and equipment create opportunities for contact spread. At the same time, crowded classes and heavy breathing can increase exposure to respiratory particles.
Wipe equipment, cover cuts, avoid sharing personal items, improve air circulation, and skip the workout when sick. Your personal record can wait; the bacteria are not awarding medals.
Setting-specific recommendations align with CDC school guidance, Cleveland Clinic contact-spread advice, and OSHA workplace controls.
Common Myths About Contact and Airborne Spread
Myth 1: If a Disease Is Airborne, Surfaces Never Matter
An airborne route may dominate, but respiratory secretions can still contaminate hands and nearby objects. Surface transmission may be less important for some pathogens, yet basic hygiene remains useful, especially in homes, schools, clinics, and food-preparation areas.
Myth 2: If I Do Not Touch the Sick Person, I Am Safe
Avoiding touch may reduce direct-contact risk, but it does not eliminate inhalation risk in shared air. Exposure duration, room size, ventilation, activity level, distance, and the pathogen involved can all affect transmission.
Myth 3: Every Disease With a Cough Is Airborne
A cough is a symptom, not a transmission classification. Some illnesses spread mainly through close respiratory contact, some through airborne particles, some through body fluids, and some through several routes. Diagnosis matters.
Myth 4: Gloves Replace Handwashing
Gloves can become contaminated, tear, or transfer germs from one surface to another. They are useful when selected for the right task, but hands should still be cleaned after glove removal.
Myth 5: Disinfecting Everything Is Always Best
Cleaning should be targeted and safe. Excessive chemical use can irritate the skin and lungs, damage household surfaces, and distract from higher-impact controls such as ventilation, vaccination, isolation, or covering an infected wound.
Myth 6: Airborne Means the Germ Stays Infectious Forever
Airborne particles may remain suspended, but a pathogen’s survival depends on environmental conditions and its biological characteristics. The concentration usually decreases as particles settle, are filtered, are removed by ventilation, or lose their ability to cause infection.
When to Get Medical Advice
Contact a healthcare professional when symptoms are severe, rapidly worsening, unusual, or occurring after a known exposure to a serious infection.
Seek prompt medical care for:
- Trouble breathing or severe shortness of breath
- Persistent chest pain or pressure
- Confusion, fainting, or difficulty waking
- Bluish or gray lips, skin, or nail beds
- Severe dehydration
- A stiff neck with fever or severe headache
- A rapidly spreading, painful, blistering, or purple rash
- Increasing wound redness, swelling, warmth, pus, fever, or red streaks
People who are pregnant, immunocompromised, very young, older, or living with chronic heart or lung disease may need earlier guidance.
Call before arriving at a clinic if measles, tuberculosis, chickenpox, or another highly transmissible illness is possible. Advance notice helps medical staff protect other patients and select appropriate isolation precautions.
Practical Experiences and Lessons From Real-World Situations
Everyday experience shows that people often choose precautions based on what is easiest to see. A dirty surface looks threatening, so it receives immediate attention. Shared air is invisible, so it may be ignored even when 20 people are talking in a closed room for two hours.
The result is sometimes “hygiene theater”: everyone wipes the same table repeatedly while the windows remain shut and the air purifier sits unplugged behind a decorative plant.
Consider a household in which one child develops ringworm. The most useful response is not to fog the living room with disinfectant. It is to treat the infection as directed, avoid skin-to-skin contact with the affected area, keep the rash covered when appropriate, wash hands after applying medication, launder towels and bedding, and stop siblings from sharing clothing or sports gear. The prevention plan follows the contact route.
Now imagine that another household member develops influenza-like symptoms. Cleaning the remote control is reasonable, but the family may gain more protection by reducing close indoor contact, improving ventilation, running a suitable air cleaner, wearing well-fitting masks during necessary interactions, and protecting anyone at higher risk of complications. The prevention plan shifts because respiratory particles are central.
Workplaces provide another common lesson. A brief elevator ride with a sick coworker is not identical to sitting beside that coworker in a windowless meeting for an entire afternoon. Exposure is shaped by time, distance, airflow, room volume, the number of occupants, and respiratory activity.
A person speaking loudly during a presentation may release more respiratory particles than someone quietly reading emails. That does not make every meeting dangerous. It means risk operates on a sliding scale rather than as an on-off switch.
Gyms demonstrate why mixed strategies matter. A fungal skin infection can spread through contact with contaminated mats or shared towels. At the same time, a crowded indoor cycling class creates heavy breathing and sustained shared-air exposure.
Cleaning equipment addresses one route. Ventilation and staying home while ill address another. Choosing only one measure leaves a gap large enough for germs to stroll through wearing tiny sneakers.
Healthcare settings make the route distinction especially visible. Staff members do not use identical precautions for every infection. Contact precautions may involve gowns and gloves, while airborne precautions may require specialized rooms and fit-tested respirators.
These measures do not necessarily mean that one disease is “scarier” than another in every respect. They are engineering and behavioral responses designed around how each pathogen travels.
The most transferable lesson is to ask three questions: Where is the pathogen leaving the infected person? How is it traveling? Where can it enter the next person?
If it leaves through a draining wound and reaches another person’s broken skin, interrupt touch. If it leaves in exhaled particles and reaches another person’s respiratory tract, improve the air and reduce inhalation. When experts say several routes are possible, layer the precautions.
Good infection prevention is rarely dramatic. It is a series of boring but effective choices: washing hands at the right time, opening a window, replacing a filter, covering a wound, staying home when sick, getting recommended vaccines, and using a mask when the situation calls for one.
Germs may have complicated travel plans, but they can still be seriously inconvenienced by humans who understand the map.
Conclusion
The central difference in direct contact vs. airborne illness is the pathway from an infected source to a susceptible person. Contact transmission depends on physical transfer through skin, fluids, wounds, mucous membranes, or contaminated objects. Airborne transmission depends on infectious particles entering shared air and being inhaled.
These routes are useful categories, not airtight boxes. Many respiratory infections can spread through a combination of inhalation, close-range particles, contaminated hands, and direct contact with secretions.
Effective prevention therefore begins with the dominant transmission route without ignoring other plausible pathways. Clean hands and shared items where contact matters. Improve ventilation, filtration, masking, and distance where inhalation matters. Add vaccination, responsible isolation, and timely medical care to create a stronger layered defense.
Research was synthesized from more than 10 reputable U.S. medical, scientific, occupational-safety, and public-health resources, including CDC, NIH, EPA, OSHA, ASHRAE, Mayo Clinic, Cleveland Clinic, Johns Hopkins Medicine, and Harvard Health.


