Myelodysplastic syndromes, often shortened to MDS, can sound like a medical term invented during a particularly intense Scrabble tournament. But behind the long name is a real group of bone marrow disorders that affect how the body makes blood cells. In MDS, the bone marrowthe soft, blood-making factory inside your bonesdoes not produce enough healthy red blood cells, white blood cells, and platelets. The result can be anemia, infections, bruising, bleeding, fatigue, and a lot of understandable questions.
The good news is that MDS treatment has become more personalized. Doctors no longer look only at a blood count and shrug dramatically. Today, care teams consider the MDS subtype, chromosome changes, gene mutations, blast percentage, transfusion needs, age, symptoms, overall health, and whether the disease is lower-risk or higher-risk. Treatment may focus on easing symptoms, improving blood counts, reducing transfusions, slowing disease progression, or, in selected cases, aiming for long-term remission or cure with a stem cell transplant.
This guide explains the main treatment options for myelodysplastic syndromes in plain English, with enough detail to be useful but not so much jargon that your coffee files a formal complaint.
Understanding the Goals of MDS Treatment
MDS treatment is not one-size-fits-all. Two people may both have MDS and still need very different care plans. One person may simply need monitoring for a while, while another may need medication, regular transfusions, or evaluation for a stem cell transplant.
Lower-risk vs. higher-risk MDS
Doctors often divide MDS into lower-risk and higher-risk categories. Lower-risk MDS usually grows more slowly and may be managed for years with supportive care and medications that improve blood counts. Higher-risk MDS has a greater chance of progressing to acute myeloid leukemia, also called AML, and may require more active disease-modifying treatment.
Risk scoring systems may include blood counts, bone marrow blast percentage, cytogenetic findings, and molecular mutations. In everyday language, this means the care team studies how the marrow is behaving, what the abnormal cells look like, and what genetic clues may predict the disease’s future behavior.
Main goals of treatment
The major goals of MDS treatment include improving quality of life, reducing fatigue, lowering infection and bleeding risks, decreasing the need for blood transfusions, preventing complications such as iron overload, slowing disease progression, and considering curative treatment when appropriate.
For many people, the first victory is not dramatic. It may be having more energy to walk the dog, fewer transfusion appointments, or enough stamina to enjoy dinner without feeling like bedtime arrived at 6:30 p.m.
Watchful Waiting: When Treatment Does Not Start Right Away
Some people with lower-risk MDS and mild symptoms may not need immediate treatment. This approach is often called watchful waiting, active surveillance, or observation. It does not mean doing nothing. It means the care team monitors blood counts, symptoms, and bone marrow changes while avoiding unnecessary side effects from treatment too early.
During watchful waiting, patients may have regular complete blood counts, physical exams, and follow-up visits. If anemia worsens, infections increase, platelets drop, or symptoms become harder to live with, the treatment plan may change.
Think of it less like ignoring a leaky faucet and more like watching the weather radar. You do not build an ark for every cloud, but you do keep an eye on the storm system.
Supportive Care for MDS
Supportive care is a foundation of MDS treatment. It does not necessarily attack the abnormal marrow cells directly, but it helps manage the problems MDS causes. For many patients, supportive care is what makes daily life more manageable.
Blood transfusions
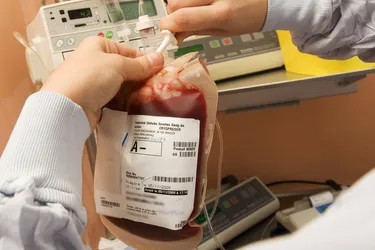
Red blood cell transfusions can help treat anemia, which is one of the most common problems in MDS. Anemia may cause fatigue, weakness, shortness of breath, dizziness, chest discomfort, or a racing heartbeat. A transfusion can temporarily increase red blood cell levels and help people feel more functional.
Platelet transfusions may be used when platelet counts are very low or when bleeding risk is high. Platelets help blood clot, so low platelet counts can lead to easy bruising, nosebleeds, bleeding gums, or prolonged bleeding from small cuts.
Iron chelation therapy
Repeated red blood cell transfusions can cause iron to build up in the body. Too much iron may affect organs such as the liver and heart. For people who need ongoing transfusions, doctors may consider iron chelation therapy, which helps remove excess iron. This is not needed for everyone, but it can be important for patients expected to receive transfusions over a long period.
Growth factors
Growth factors are medicines that encourage the bone marrow to make more blood cells. Erythropoiesis-stimulating agents, often called ESAs, may help some people with anemia produce more red blood cells. These medicines tend to work best in selected lower-risk patients, especially those with lower natural erythropoietin levels and less intense transfusion needs.
Other growth factors may be used in certain situations to support white blood cell production, especially if infections become a major concern. The goal is not to turn the marrow into a superhero overnight, but to nudge it toward doing its job better.
Antibiotics and infection prevention
When white blood cells are low or not working properly, infection risk can rise. Treatment may include prompt antibiotics, vaccines when appropriate, and practical prevention strategies such as hand hygiene, avoiding sick contacts, and calling the care team quickly for fever. In MDS, a fever is not something to “sleep off” like a bad movie choice.
Medications for Lower-Risk MDS
Lower-risk MDS treatment often focuses on improving blood counts, especially anemia. The best option depends on transfusion needs, chromosome changes, prior treatment, and whether the person has ring sideroblasts or other specific marrow findings.
Erythropoiesis-stimulating agents
ESAs such as epoetin alfa or darbepoetin alfa may be used to treat anemia in certain lower-risk MDS patients. They work by encouraging red blood cell production. Not everyone responds, and the care team usually monitors hemoglobin levels and transfusion needs to decide whether the treatment is helping.
Luspatercept
Luspatercept is used for anemia in certain adults with very low- to intermediate-risk MDS who may require regular red blood cell transfusions. It helps improve red blood cell maturation, which can reduce transfusion needs in selected patients. It may be especially relevant for people with ring sideroblasts, though approved use has expanded in recent years for some patients before ESA use.
Lenalidomide for deletion 5q MDS
Lenalidomide is an oral medication that can be very effective for certain patients with lower-risk MDS associated with a deletion 5q chromosome abnormality. In this group, it may reduce or eliminate transfusion needs for some people. It can also lower blood counts at first, so careful monitoring is important.
Imetelstat
Imetelstat is a newer option for adults with low- to intermediate-1 risk MDS with transfusion-dependent anemia who have not responded to, have lost response to, or are not eligible for ESAs. It works as a telomerase inhibitor, which is a fancy way of saying it targets a mechanism abnormal cells may use to keep dividing. It is not a casual vitamin; it requires specialist oversight and monitoring for side effects such as low blood counts.
Immunosuppressive therapy
Some selected patients may benefit from immunosuppressive therapy, such as antithymocyte globulin or cyclosporine. This approach may be considered when the immune system appears to be contributing to bone marrow failure. It is not used for every MDS patient, but in carefully chosen cases, it may improve blood counts.
Treatment for Higher-Risk MDS
Higher-risk MDS usually requires a more active strategy because the disease is more likely to worsen or progress to AML. Treatment may aim to slow progression, improve survival, control symptoms, and prepare eligible patients for stem cell transplant.
Hypomethylating agents
Hypomethylating agents, also called HMAs, are commonly used for higher-risk MDS. The two best-known medicines in this category are azacitidine and decitabine. These drugs affect how abnormal marrow cells regulate genes, which may help the marrow produce healthier cells and slow the disease.
HMAs are usually given in cycles, and patients often need several cycles before doctors can judge whether the treatment is working. Blood counts may temporarily worsen before improving, which can be frustrating. This is one of those times when the treatment calendar may feel like a slow-loading webpage, but patience and close monitoring matter.
Oral decitabine and cedazuridine
Some patients may be candidates for an oral combination of decitabine and cedazuridine. This option can offer a more convenient way to receive HMA-type therapy for certain adults with MDS, though it still requires careful lab monitoring and specialist supervision.
Intensive chemotherapy
For selected fit patients, especially those with high blast counts or MDS behaving more like AML, doctors may consider intensive chemotherapy. This approach is stronger and usually carries more risk, including infections, low blood counts, hospitalization, and significant side effects. It may be used as a bridge to stem cell transplant in appropriate patients.
Stem Cell Transplant for MDS
An allogeneic stem cell transplant, sometimes called a bone marrow transplant, is generally considered the only treatment with curative potential for MDS. “Allogeneic” means the stem cells come from a donor, not from the patient. The donor may be a matched sibling, unrelated donor, or sometimes another donor source depending on the transplant center and patient situation.
Stem cell transplant is powerful, but it is not simple. It may involve chemotherapy, immune-suppressing medicines, infection risk, graft-versus-host disease, relapse risk, and a long recovery. Because of these risks, transplant is usually considered for patients who are healthy enough to tolerate it and whose disease risk makes the potential benefit worth considering.
Reduced-intensity transplant approaches may be options for some older adults or people who cannot tolerate the most intensive conditioning regimens. The decision requires detailed discussion with an MDS specialist and transplant team.
Clinical Trials and Emerging MDS Treatments
Clinical trials are an important part of MDS care, especially when standard treatments stop working or when the disease has high-risk features. Trials may study new drug combinations, targeted therapies, immune-based treatments, maintenance therapy after transplant, or treatments tailored to genetic mutations.
For example, researchers continue to investigate therapies for difficult-to-treat disease biology, such as TP53-mutated MDS, as well as combinations involving hypomethylating agents. Not every promising idea becomes a standard treatment, but clinical trials are how better options move from “interesting science” to “available care.”
Patients should ask whether a clinical trial is appropriate at diagnosis, before changing therapy, and after relapse or loss of response. Asking about trials is not a sign of desperation. It is a sign that you want to know the full menu before ordering.
How Doctors Choose the Right MDS Treatment
Choosing treatment for myelodysplastic syndromes involves balancing disease risk and patient priorities. A 72-year-old with mild anemia and lower-risk MDS may need a different plan than a 58-year-old with higher-risk MDS and rising blasts. A person who values fewer clinic visits may make different choices than someone who is willing to accept more side effects for a chance at deeper disease control.
Factors that guide treatment
Important decision-making factors include MDS risk category, blood count levels, transfusion dependence, symptoms, bone marrow blast percentage, chromosome abnormalities, gene mutations, age, kidney and liver function, heart health, infection history, prior treatments, donor availability, and personal preferences.
Good MDS care also includes honest conversations. Patients should feel comfortable asking: What is the goal of this treatment? How will we know if it is working? What side effects should I report quickly? Are there alternatives? Should I get a second opinion at a center that treats many MDS patients?
Managing Side Effects and Daily Life During MDS Treatment
MDS treatment can affect everyday life. Some medicines may cause nausea, diarrhea, constipation, fatigue, injection-site reactions, low blood counts, infections, or changes in appetite. Transfusions can take time and may require planning around work, transportation, and family responsibilities.
Patients can often improve their experience by keeping a symptom journal, tracking transfusion dates, bringing an updated medication list to appointments, asking about fever instructions, and reporting new bleeding, shortness of breath, chest pain, confusion, or severe weakness right away.
Nutrition, movement, sleep, and emotional support also matter. No smoothie can cure MDSif it could, hematologists would own a lot more blendersbut staying as strong as possible can help people tolerate treatment better.
Experiences Related to MDS Treatment Options
Living with MDS treatment is often less like one dramatic hospital scene and more like a long-running series with recurring characters: the hematologist, the lab technician, the infusion nurse, the calendar app, and that one chair in the waiting room that becomes oddly familiar. Many patients describe the beginning as the hardest part because the diagnosis arrives with unfamiliar words, uncertain timelines, and treatment choices that sound both hopeful and intimidating.
One common experience is learning to measure progress differently. Before MDS, a good week may have meant finishing a project, taking a trip, or getting through the grocery store without forgetting the eggs. During treatment, a good week may mean hemoglobin held steady, no transfusion was needed, platelets behaved themselves, or fatigue improved enough for a walk around the block. These may sound like small victories, but for someone managing bone marrow disease, they can feel enormous.
Transfusion-based care can become a routine. Patients may learn which snacks travel well, which sweater works in chilly infusion rooms, and how to schedule appointments around the days when energy tends to dip. Some people feel better quickly after red blood cell transfusions, while others notice a slower improvement. Caregivers often become unofficial logistics managers, tracking lab results, medication changes, appointment times, insurance calls, and parking validation like Olympic-level administrators.
Medication experiences vary widely. A person taking an ESA may wait weeks to see whether red blood cell production improves. Someone starting luspatercept or imetelstat may focus on whether transfusion needs decrease. Patients receiving azacitidine or decitabine may go through cycles where blood counts drop before the treatment benefit becomes clear. This waiting can be emotionally exhausting because the body does not always send a polite email explaining what it is doing.
Stem cell transplant discussions can bring a different emotional weight. For some, transplant represents hope for long-term remission or cure. For others, the risks feel overwhelming. Patients may need time to understand donor matching, conditioning therapy, hospital stays, graft-versus-host disease, relapse risk, and recovery. A second opinion from a transplant center can help people feel more confident, whether they choose transplant or not.
Many people also discover that communication is treatment. Asking questions, reporting symptoms early, and telling the care team what matters personally can shape the plan. For example, one patient may prioritize fewer transfusions to regain independence, while another may prioritize avoiding side effects that interfere with caregiving, work, or travel. Neither approach is “wrong.” Good MDS care should make room for medical facts and real life.
Emotional support is another major part of the experience. MDS can create anxiety because it is chronic, unpredictable, and sometimes progressive. Support groups, counseling, patient organizations, and honest family conversations can help. People do not need to become full-time cancer experts overnight. They only need to keep learning enough to make the next decision with their care team.
In the end, the MDS treatment journey is personal. Some days are clinical and numbers-focused; others are emotional and messy. The best plans usually combine evidence-based medicine, careful monitoring, practical support, and respect for the patient’s goals. That combination can make a complicated diagnosis feel more manageableone appointment, one lab result, and one well-earned nap at a time.
Conclusion
Myelodysplastic syndromes are complex, but treatment options have become more thoughtful and personalized. Some patients need watchful waiting, while others benefit from transfusions, growth factors, luspatercept, lenalidomide, imetelstat, hypomethylating agents, chemotherapy, stem cell transplant, or clinical trials. The right plan depends on risk level, symptoms, blood counts, genetics, overall health, and personal goals.
The most important step is working with an experienced hematology team that can explain the purpose of each treatment, monitor response, adjust the plan, and help patients protect quality of life. MDS may be complicated, but patients do not have to navigate it alone.
Medical note: This article is for educational purposes only and does not replace professional medical advice. People with MDS should discuss diagnosis, treatment options, side effects, and clinical trial opportunities with a qualified hematologist or oncology care team.


